


Polyarteritis nodosa (PAN) is a condition that causes swollen arteries. It primarily affects small and medium arteries, which can become inflamed or damaged. This is a serious disease of the blood vessels caused by an immune system malfunction.
Ongoing treatment is crucial, and there’s a risk of serious complications for people who have it and don’t seek medical care.
PAN ultimately affects all of your organs, including the skin. It can also affect your central nervous system.
The symptoms of PAN are quite pronounced and may include:
According to Johns Hopkins, PAN affects the nervous systems of up to 70 percent of people. Without medical treatment, PAN can cause seizures and neurological issues, including reduced alertness and cognitive dysfunction, after two to three years.
Skin lesions are also very common. PAN most often affects the skin on the legs, and the sores can be painful.
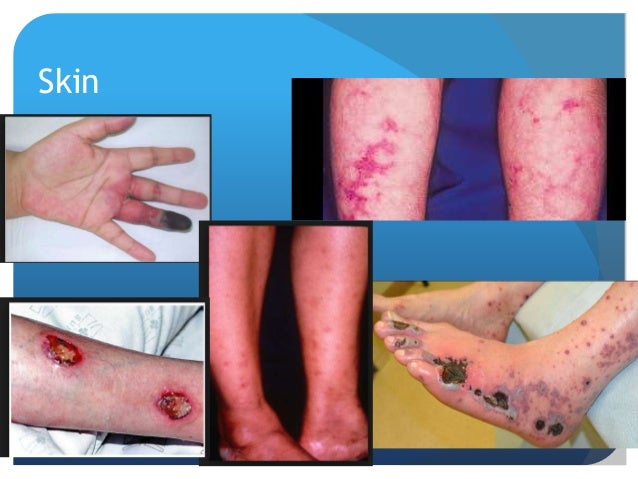
Your arteries carry blood to your tissues and organs. PAN is characterized by damaged arteries that impede the flow of blood to the rest of your body. When your organs don’t receive enough oxygen-rich blood, they stop working the way they should. This type of arterial damage occurs when your immune system attacks your arteries. There’s no one identifiable cause for this immune reaction, so the exact cause of PAN also remains unknown.
While the exact cause of PAN is unknown, there are many factors that can increase your risk of developing the disease. PAN is more common in people who:
It’s important to understand these risk factors and talk to your doctor about receiving regular tests. This is especially true if you experience symptoms of PAN or if the condition runs in your family.
PAN is a complicated disease that requires multiple tests before your doctor can make a proper diagnosis. Your doctor will likely order a complete blood count to measure the number of red and white blood cells you have.
You may also undergo:
Most people with PAN have elevated ESR results. According to Johns Hopkins, skin and muscle or nerve biopsies can be helpful when making a diagnosis.
Once these tests are complete, your doctor will formulate a diagnosis and treatment plan.
In some cases, doctors may mistake abdominal pain and gastrointestinal side effects for inflammatory bowel disease. For this reason, it’s important to report any long-term gastrointestinal effects to your doctor right away.
The most common treatment for PAN is a combination of prescription drugs, including:
High doses of corticosteroids, or steroids, control the symptoms of PAN by reducing inflammation and replacing certain hormones in the body. Corticosteroids can cause a number of side effects, especially when they’re taken in the oral form.
Corticosteroids can help keep your immune system from attacking your arteries, but other types of immunosuppressive medications may be necessary. This is especially true if your PAN symptoms are severe.
People with hepatitis infections primarily receive antiviral medications.
Conditions affecting the blood vessels are very serious. Damaged arteries can ultimately affect your brain, heart, and other vital organs.
The most common complications of PAN include:
CAUSES OF HEARING LOSS IN ADULTS:
Hearing loss in adults has many causes such as, exposure to noise, disease or infection, ototoxic drugs, tumors, trauma and the aging process. Some examples of causes of hearing loss in adults are described below:
Presbycusis is the most common cause of sensory hearing loss in the adult population. This loss is caused by some degenerative changes (in the auditory system) associated with the aging process. The hearing loss is progressive in nature with the high frequencies affected first. While the process begins after age 20-30, it is often at ages 55 to 65 that the high frequencies in the speech range begin to be affected.
This is the second most common cause of acquired sensorineural hearing loss. Prolonged exposure to loud noise causes damage to the hair cells in the cochlea and results in this type of permanent hearing loss. The noise-induced hearing loss usually develops gradually and painlessly. Sometimes the hearing loss can occur as a result of an acoustic trauma, or a single exposure or very few exposures to very high levels of sound. When this happens, a complete breakdown of the Organ of Corti in the inner ear occurs. When the hair cells become damaged from prolonged exposure to loud noises such as music, machines, motors and other noise producing equipment or to a single but very loud noise exposure such as gunfire or an explosion, they are unable to be stimulated properly by an incoming sound signal. Once these hair cells have become damaged there is no way for them to be repaired.
This is the condition often referred to as an ear infection. When otitis media occurs, fluid accumulates behind the eardrum in the middle ear space. This space is normally air filled in a healthy ear. The fluid arises because of the inability of the Eustachian tube to adequately function and keep the pressure equalized to atmospheric pressure in the middle ear space. The Eustachian tube dysfunction can be the result of allergies, infection in the upper respiratory tract.
This is a progressive ear disease involving the middle ear bony capsule, specifically affecting the movement of the stapes (one of the three small bones in the middle ear).
This is an inner ear disease and is characterized by progressive fluctuating sensorineural hearing loss, vertigo (dizziness) , and tinnitus (ringing in the ear).
Drugs used to treat some diseases are damaging to the auditory system (ototoxic) and cause hearing loss. The more common drugs that are particularly toxic to the ear are certain antibiotics (such as Streptomycin, Kanamycin, Neomycin), Salicylates in large quantities (drugs containing aspirin), and quinine. Some drugs used in chemotherapy regimens are reported to be ototoxic. The damage caused by these drugs often depends on the dose administered and length of time used and is usually permanent.
This is an example of a tumor that causes sensorineural hearing loss. Acoustic neuromas arise in the 8th cranial nerve (acoustic nerve). The first symptom could be a unilateral hearing loss, tinnitus in one ear, or vertigo.
Trauma can cause a conductive, sensorineural or even a mixed hearing loss. Damage can occur to the as a result of trauma to the ear itself or to the side of the head. Examples include fractures of the temporal bone, puncture of the ear drum by foreign objects, , and sudden changes in air pressure.
This is an abrupt loss of hearing. Sudden hearing loss of known causes may be due to drugs, trauma, infection, or disease. There are, however, many instances when no cause can be found. There are two theories as to what happens in these cases: Vascular Occlusion which is the abrupt interference of blood supply to the cochlea and Viral Labrynthitis (viral infection of the inner ear), which produces damage to the inner ear structures.

Hearing loss occurs in most people as they age. It is not always easy to notice at first. That is why many people have a difficult time believing and accepting, that they have a hearing loss. People might begin turning up the volume on the TV, or asking other people to repeat themselves.
When their hearing starts to fade, people tend to forget how things sound. They start to live in a quieter world, unaware that they are missing the softer sounds of everyday life, like the pattern of rain on the roof or the sound of birds singing.

Treatment Options For Tinnitus:
There are a variety of treatment options available that may help relieve your tinnitus symptoms ranging from physical products like hearing aids, to counselling to help deal with adverse emotional side effects such as depression and anxiety. Discuss with your audiologist what the best course of action is for your specific case of tinnitus.
Good quality and properly fitted hearing aids reduce and even eliminate most tinnitus associated with hearing losses. Hearing aids take away the strain of listening and distract from the tinnitus by bringing you more environmental sounds from the outside world. Click here to view some of the available styles from Oticon and Phonak.
Therapeutic Noise Generator devices which look like hearing aids and are recommended for people with no hearing loss. These devices produce a blend of external sounds which stimulate most fibres of the hearing nerve, helping to deviate attention away from the tinnitus.
Tinnitus Retraining Therapy (TRT) aims to reduce and ultimately eliminate tinnitus perception. It combines auditory therapy (hearing aids and/or therapeutic noise generators), to provide the brain with maximum environmental sounds to reduce tinnitus perception. Directive counselling or cognitive behavioural therapy helps to change negative beliefs about tinnitus, distract you from focusing too much on the condition, and reduce stress.
There are no specific medications for the treatment of tinnitus. Sedatives and some other medications may prove helpful in the early stages for some people depending on the cause of the tinnitus. Vitamin B12 may be helpful and herbal remedies, if taken under medical supervision, may be of some use.
For the vast majority of people there is no specific surgical treatment for tinnitus. However, following successful surgical treatment for some ear problems e.g. otosclerosis, Meniere’s disease, middle ear infection, an existing tinnitus problem may sometimes disappear.
Vitamin B9 includes both folate and folic acid and is important for several functions in the body.
Folic acid is vital for making red blood cells, as well as:
It is particularly important for women who are pregnant to consume enough folic acid. This helps prevent the fetus from developing major congenital deformities of the brain or spine, including neural tube defects, such as spina bifida and anencephaly.
Women planning to get pregnant should take folic acid supplements for a full year before conception to reduce the risk of these developments.
Folic acid is thought to play a preventive role in a range of conditions.

Types of diseases which causes by deficiency of Folic acid as follows:
Autism
A recent study connected folic acid deficiency with autism. The investigators concluded: “Periconceptional folic acid [before conception and during early pregnancy] may reduce [autism spectrum disorder] risk in those with inefficient folate metabolism.”
A literature review carried out in 2014 concluded that folic acid supplementation might reduce the risk of a cleft palate.
Folic acid is often used to support a methotrexate prescription for rheumatoid arthritis.
Methotrexate is an effective medicine for this condition. However, it is also known to remove folate from the body. This can cause gastrointestinal symptoms for between 20 and 65 percent of people who use the drug.
However, folic acid supplements have been shown to reduce the gastrointestinal side effects of methotrexate by 79 percent. Speak to a doctor for recommendations on how much to take, and how often. 1 milligram (mg) per day is often prescribed.
Folic acid deficiency occurs when not enough folate or folic acid is present in the body.
Aside from anemia and congenital deformities, folic acid deficiency can result in other health problems, including:
The Medical Journal of Australia advised in January 2011 that the prevalence of folate deficiency in the country had dropped considerably since introducing the compulsory fortification of wheat flour in breadmaking.
Individuals can develop folic acid deficiency anemia if they do not consume enough folic acid.
As folate is important for producing and maintaining red blood cells, inadequate levels can mean that there are not enough red blood cells to supply the body with a healthy level of oxygen.
This condition can appear in people who require higher quantities of folate and are not taking supplements, such as women who are pregnant and lactating.
Folic acid deficiency anemia can occur in people with underlying conditions, such as sickle cell anemia. It can also affect people with conditions that affect folate absorption. Alcohol abuse or kidney disease can reduce the ability of the body to effectively absorb folate.
Some medications, such as those used for treating rheumatoid arthritis, cancer, and seizures, may increase the risk of folic acid deficiency anemia.
The signs and symptoms of folic acid deficiency disease include:
People with folic acid deficiency anemia are given folic acid pills for daily use. Once folate levels return to normal, the body can produce enough blood cells to allow normal function.
There are no serious side effects when taking folic acid. In rare cases, individuals report an upset stomach.
Even if a person takes more folate than needed, there is no cause for concern. Because folic acid is water-soluble, any excess will be naturally passed in urine.
All women who are pregnant or planning to become pregnant should consume more folic acid, according to March of Dimes, a research organization focused on preventing deformity and death in newborn infants.
They also recommend that women take folic acid before getting pregnant as well as during the first 4 weeks following conception.
Every woman capable of getting pregnant should be taking daily folic acid supplements. Women over the age of 14 years should take 400 micrograms (mcg) per day, and this should increase to 600 mcg during a pregnancy.
Women should maintain a daily intake of 500 mcg.
Multiple Sclerosis – Literally, “many hardenings,” MS is a disease of unknown cause that manifests as multiple hard plaques of degeneration of the insulating layer of nerve fibers in the central nervous system. The loss of insulation allows “short circuiting” of nerve impulses. Depending upon where the degeneration occurs, patients may suffer paralysis, sensory disturbances or blindness.
 Cerebrovascular accident (CVA) – the fancy name for a “stroke”. A blood vessel in the brain may burst causing internal bleeding. Or, a clot may arise in a brain blood vessel (a thrombus), or arise elsewhere (embolus) and travel to get stuck in a brain vessel which then deprives brain tissue of oxygen. Depending upon the area of the brain involved, the patient may suffer paralysis, loss of speech or loss of vision.
Transient Ischemic Attack (TIA) – “Ischemia” was introduced previously in the circulatory diseases module referring to the heart. It literally means “not quite enough blood”. A short period of insufficient blood supply to the brain can have the same signs and symptoms as a stroke such as weakness in an arm, a partial loss of vision, but the problem lasts less than 24 hours. People who get TIA’s are at increased risk of having a stroke in the future.
Epilepsy – a Greek word for “seizure.” Convulsions is another term used. Seizures may have many causes and not all seizures are epilepsy. High fevers in young children may trigger seizures which are short in duration, easily controlled and, typically, have no permanent aftereffects. Epilepsy is a specific condition which may occur at any age, seizures are more intense, longer lasting in duration, and recur with some frequency. The condition may be controlled with medication, or if unresponsive to drugs, may require surgery.
Aphasia – loss of speech. The speech centers are located on the left side of the brain in a majority of people. If someone suffers a “stroke” (cerebrovascular accident-CVA), or traumatic brain injury, and it involves the left side of the brain, they may suffer speech impediments that vary over a spectrum of problems from difficulty in finding the right word, speaking slowly and with difficulty, or complete loss of speech. Actually, there are two speech centers. Injury described above involves the motor speech area, the area of the brain that produces language by integrating thoughts of speech with the movements of the larynx, lips and tongue. There is a second speech area, the receptive or sensory area, that enables us to understand speech. Injury to the latter results in still fluent speech, but the individual does not understand what they are hearing.
Neuronal ceroid lipofuscinosis (NCL) refers to a group of conditions that affect the nervous system. Signs and symptoms vary widely between the forms but generally include a combination of dementia, vision loss, and epilepsy. Although the NCLs were historically classified according to their age of onset and clinical features, the most recent classification system is primarily based on their underlying genetic cause. Most forms are inherited in an autosomal recessive manner; however, autosomal dominant inheritance has been reported in one adult-onset form (neuronal ceroid lipofuscinosis 4B). Treatment options are limited to therapies that can help relieve some of the symptoms.
Lipofuscinoses are inherited as autosomal recessive traits. NCLS involves the buildup of an abnormal material called lipofuscin in the brain. NCLS is thought to be caused by problems with the brain’s ability to remove and recycle proteins.
The Human Phenotype Ontology (HPO) provides the following list of features that have been reported in people with this condition. If available, the list includes a rough estimate of how common a feature is (its frequency). Frequencies are based on a specific study and may not be representative of all studies.
| Signs and Symptoms | Approximate number of patients (when available) |
| Abnormal electroretinogram | Very frequent (present in 80%-99% of cases) |
| Abnormality of the retinal vasculature | Very frequent (present in 80%-99% of cases) |
| EEG abnormality | Very frequent (present in 80%-99% of cases) |
| Intellectual disability | Very frequent (present in 80%-99% of cases) |
| Mental deterioration | Very frequent (present in 80%-99% of cases) |
| Muscular hypotonia | Very frequent (present in 80%-99% of cases) |
| Ocular albinism | Very frequent (present in 80%-99% of cases) |
| Seizures | Very frequent (present in 80%-99% of cases) |
| Visual impairment | Very frequent (present in 80%-99% of cases) |
| Visual loss | Very frequent (present in 80%-99% of cases) |
The person may become totally dependent on others for help with daily activities.
Treatments:


Anencephaly is one of the most common neural tube defects. Neural tube defects are birth defects that affect the tissue that grows into the spinal cord and brain.
Anencephaly occurs early in the development of an unborn baby. It results when the upper part of the neural tube fails to close. Why this happens is not known. Possible causes include environmental toxins and low intake of folic acid by the mother during pregnancy.
Anencephaly occurs in about 1 out of 10,000 births. The exact number is unknown, because many of these pregnancies result in miscarriage. Having one infant with this condition increases the risk of having another child with neural tube defects.

There is no current therapy. Talk to your doctor about care decisions.
It is important for women who may become pregnant to get enough folic acid.
There is good evidence that folic acid can help reduce the risk of certain birth defects, including anencephaly. Women who are pregnant or planning to become pregnant should take a multivitamin with folic acid every day. Many foods are now fortified with folic acid to help prevent these kinds of birth defects.
Getting enough folic acid can reduce the chance of neural tube defects by 50 percent.
For specific recommendations, see folic acid (folate).
This rare type of headache doesn’t stop. It causes pain on one side of your face or head.
Doctors don’t know what causes this “continuous headache.” But women seem to get it more often than men.
With the right treatment, though, most people can get nearly complete relief from the pain.
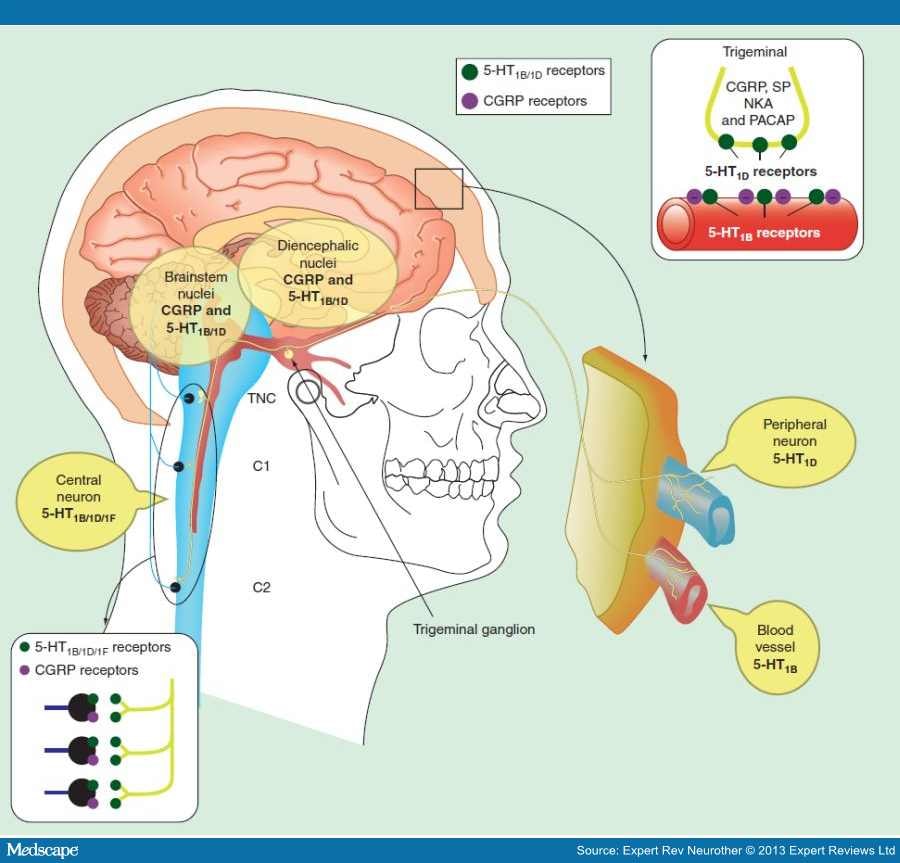
People with hemicrania continua describe a dull ache or throb that’s interrupted by pain that is:
These attacks usually happen three to five times a day.
Some people will have these headaches steadily for months or years. For others, the pain will go away for weeks or months, then come back.
The headaches often have some of the same symptoms as other kinds. This overlap can make them tricky for doctors to diagnose.
Like migraines, they can cause:
Hemicrania continua also shares features of cluster headaches. For example, people who have it may have problems with how part of their nervous system works. That causes symptoms that happen on the painful side of the face and head, including:
Some things tend to make symptoms worse, such as:
About 10% of people have symptoms when they:
Doctors can make a diagnosis of hemicrania continua if you’ve had pain consistently, without it switching sides or disappearing even briefly, for at least 3 months.

Some anti-inflammatory medications ease hemicrania continua headaches. Indomethacin, a nonsteroidal anti-inflammatory drug (NSAID), often gives fast relief. One way doctors know that you have hemicrania continua is if your headaches go away after a dose of the drug. But some people may need more testing — such as an MRI — to look into their symptoms.
Daily doses of indomethacin for hemicrania continua typically range from 25 to 200 milligrams. A common side effect of the drug is irritation of the lining of the stomach and digestive tract. So, people who take it may also need medication to help their stomach make less acid.
If the side effects of indomethacin are too much for you, another NSAID, celecoxib, may also help.
Tricyclic antidepressants, like amitriptyline, can also prevent these headaches.
Amyotrophic lateral sclerosis (ALS) is a rare group of neurological diseases that mainly involve the nerve cells (neurons) responsible for controlling voluntary muscle movement. Voluntary muscles produce movements like chewing, walking, breathing and talking. The disease is progressive, meaning the symptoms get worse over time. Currently, there is no cure for ALS and no effective treatment to halt, or reverse, the progression of the disease.
ALS belongs to a wider group of disorders known as motor neuron diseases, which are caused by gradual deterioration (degeneration) and death of motor neurons. Motor neurons are nerve cells that extend from the brain to the spinal cord and to muscles throughout the body. These motor neurons initiate and provide vital communication links between the brain and the voluntary muscles.
Messages from motor neurons in the brain (called upper motor neurons) are transmitted to motor neurons in the spinal cord and to motor nuclei of brain (called lower motor neurons) and from the spinal cord and motor nuclei of brain to a particular muscle or muscles.
In ALS, both the upper motor neurons and the lower motor neurons degenerate or die, and stop sending messages to the muscles. Unable to function, the muscles gradually weaken, start to twitch (called fasciculations), and waste away (atrophy). Eventually, the brain loses its ability to initiate and control voluntary movements.
Early symptoms of ALS usually include muscle weakness or stiffness. Gradually all muscles under voluntary control are affected, and individuals lose their strength and the ability to speak, eat, move, and even breathe.
Most people with ALS die from respiratory failure, usually within 3 to 5 years from when the symptoms first appear. However, about 10 percent of people with ALS survive for 10 or more years.

It is unclear exactly what causes ALS. There are different types, according to their signs and symptoms and whether or not there is a clear genetic association.
ALS can be sporadic or familial.
Sporadic ALS occurs randomly, and it accounts for 90 to 95 percent of cases. There is no clear risk factor or cause.
Familial ALS is inherited. Around 5 to 10 percent of cases are familial. The child of a person with ALS will have a 50 percent chance of developing the condition. Rarely, it can affect a person in their teens. Researchers are investigating which genes are involved.
Other possible causes of ALS include:
Environmental factors may also play a role.
One study has reported that military personnel deployed in the Gulf region during the 1991 war were more likely to develop ALS than military personnel deployed elsewhere.
Some possible links have been found between ALS and exposure to:
However, there is no conclusive evidence that specific lifestyle changes can decrease the risk.
The symptoms of ALS usually appear when a person is in their late 50s or early 60s, but it can happen at other ages.
Progression varies between individuals. In the early stages, signs and symptoms may be barely noticeable, but the weakness becomes more visible over time.
Common symptoms include:

Progressive muscle weakness occurs in all cases of ALS, but this may not be the first indication of the condition.
Early symptoms often include clumsiness, abnormal limb fatigue, muscle cramps and twitches, and slurred speech. Symptoms will spread to all parts of the body as ALS progresses.
Some people may have problems with decision-making and memory, eventually leading to a form of dementia called frontotemporal dementia.
Emotional lability can cause fluctuations in mood and emotional response.
There is no cure for ALS, so treatment aims to alleviate symptoms, prevent unnecessary complications, and slow the rate of disease progression.
ALS can cause a range of physical, mental, and social changes, so a team of specialists will often help patients manage their symptoms and care, improve their qualify of life, and prolong survival.
Riluzole (Rilutek) was approved for ALS treatment by the Food and Drug Administration (FDA) in 1995, and it appears to slow the progression of the disease. It may work by reducing the body’s levels of glutamate, an excitotoxin that has been linked to neuronal damage.
In May 2017, Radicava (Edaravone) was approved to treat ALS. It may slow the decline in physical function by one third.
A number of research projects are looking at ways to use new and existing drugs to treat different aspects of ALS. Doctors can also prescribe medications to treat the different symptoms.
Physical therapy can help people with ALS manage pain and address mobility issues.
A physical therapist can provide help and information with:
Occupational therapy can help a patient maintain their independence for longer by:
Breathing therapy may be needed in time, as the respiratory muscles get weaker.
Breathing devices can help the patient breathe better at night. Some patients may need mechanical ventilation. One end of a tube is connected to a respirator, while the other end is inserted into the windpipe through a surgically-created hole in the neck, or tracheostomy.
Speech therapy is useful when ALS begins to make it harder to talk. Speech therapists can help by teaching adaptive techniques. Other methods of communication include writing and computer-based communications equipment.
Nutritional support is important, as difficulty with swallowing can make it hard to get enough nutrients. Nutritionists can advise on preparing nutritious meals that are easier to swallow. Suction devices and feeding tubes may help.
Mastoiditis is a bacterial infectionof the mastoid air cells surrounding the inner and middle ear. The mastoid bone, which is full of these air cells, is part of the temporal bone of the skull. The mastoid air cells are thought to protect the delicate structures of the ear, regulate ear pressure and possibly protect the temporal bone during trauma.
When the mastoid cells become infected or inflamed, often as a result of an unresolved middle ear infection (otitis media), mastoiditis can develop. Because so many vital structures pass through the mastoid, infection may spread outside of the mastoid bone and cause serious health complications.
Acute mastoiditis typically affects children, but adults can also be affected.
Some people have chronic mastoiditis, an ongoing infection of the middle ear and mastoid that causes persistent drainage from the ear.

As mentioned above, mastoiditis most often develops as a result of a middle ear infection. Bacteria from the middle ear can travel into the air cells of the mastoid bone. Less commonly, a growing collection of skin cells called a cholesteatoma, may block drainage of the ear, leading to mastoiditis.
Mastoiditis symptoms may include:
Mastoiditis complications may include:
Antibiotic therapy is the mainstay of treatment for both acute and chronic mastoiditis.
If you or your child is diagnosed with acute mastoiditis, you may be put in the hospital to receive treatment and care by an otolaryngologist, a doctor who specializes in ear, nose, and throat disorders. Antibiotics will be given through an IV (intravenous line) to treat the infection.
Surgery may also be needed to drain the fluid from the middle ear, called a myringotomy. During a myringotomy, the doctor makes a small hole in the eardrum to drain the fluid and relieve pressure from the middle ear. A small tube may be inserted into the middle ear to to keep the hole from closing so as to allow for continued drainage. Typically, the tube will fall out on its own after six to 12 months.
If the symptoms don’t quickly improve on IV antibiotics, or complications, like an abscess or bone erosion are present, surgery to remove the infected mastoid bone may be recommended. This is called a mastoidectomy.
Chronic mastoiditis is treated with oral antibiotics, eardrops, and regular ear cleanings by a doctor. If these treatments do not work, surgery may be necessary to prevent further complications.
If left untreated, mastoiditis can cause serious, even life-threatening, health complications, including hearing loss, blood clot, meningitis, or a brainabscess. But with early and appropriate antibiotic treatment and drainage, these complications can usually be avoided and you can recover completely.
If you have an earache, discharge or trouble hearing, see your doctor. He will decide if you need antibiotics to help prevent mastoiditis and other serious health complications.